Two people describe almost the same thing, a deep ache that sits somewhere between the lower back, the buttock and the top of the leg, and yet one has a problem with a nerve and the other has a problem with a joint. They will often need quite different treatment, and the word a person reaches for first (“it’s my sciatica” or “it’s my hip”) is frequently the wrong one.
The good news is that these two conditions leave different fingerprints. Once you know what to look at (where the pain travels, what sets it off, and when it bites), telling sciatica from a hip problem gets a great deal easier.
Why the two get confused: pain is a poor witness to its own cause
The reason people mix these up is that pain does not always announce where it comes from. Nerves and joints both send signals that the brain can place some distance from the actual source, a phenomenon called referred pain. A grumpy hip joint can throw an ache down into the thigh or even the knee; an irritated nerve root in the spine can light up the buttock.
The buttock, in particular, is a crowded crossroads where sciatic nerve pain, deep gluteal problems and hip-related pain all overlap, which is exactly why guessing by location alone so often misleads. The more reliable approach is to treat the pain like a trail rather than a single dot, and follow where it leads.
Follow the pain’s path: where it travels tells you what it is
The single most useful habit is to map the pain to a zone. Each of the three main culprits has a home territory, and although they can blur at the edges, the pattern points you in the right direction more often than not.
| Where you mostly feel it | What it usually points to | The tell-tale extra |
|---|---|---|
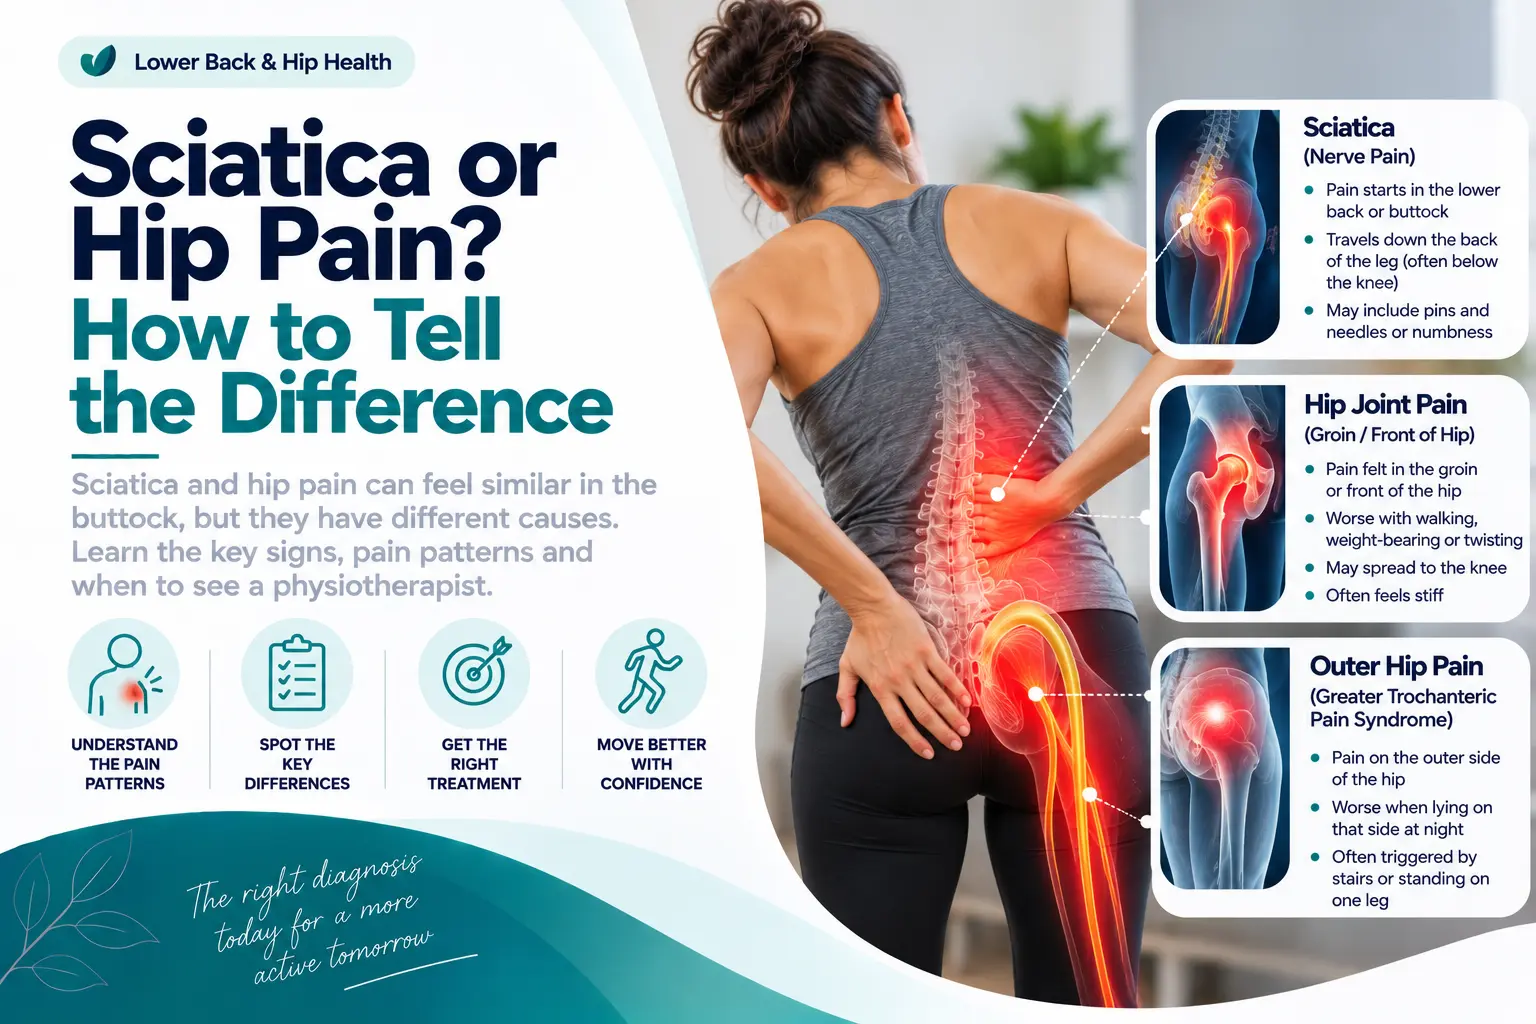
| Groin / deep front of hip | The hip joint itself (osteoarthritis, impingement) | Worse on weight-bearing, pivoting and twisting; may spread to the knee |
| Outer / side of the hip | Greater trochanteric pain syndrome (the tendons and bursa on the side) | Sharp when you lie on that side at night or climb stairs |
| Buttock, then down the back of the leg | The sciatic nerve / a lower-back nerve root | Often travels past the knee with pins and needles or numbness |
If you remember only one rule, make it this: pain that travels below the knee is far more likely to be nerve-driven, while pain that stays around the hip and groin is far more likely to be the joint. It is not infallible, but it is the quickest sorting question there is.
Pain below the knee usually follows the sciatic nerve
When the pain shoots in a line from the buttock down the back of the thigh and past the knee into the calf or foot, and especially when it comes with pins and needles, numbness or a weak-feeling leg, the sciatic nerve is the prime suspect. The source is almost never the leg itself; it is a nerve root being irritated up in the lower spine, which is why the pain flares when you cough, bend or sit for a while.
The mechanics of that, and what actually settles it, are a topic in their own right, and we cover them in our explainer on why leg pain often starts in your lower back. For the purpose of telling it apart from a hip problem, the headline feature is simple: it travels, and it travels down a defined line.
Groin and deep-front pain usually points to the hip joint
Hip-joint pain behaves very differently. Because the joint sits deep and towards the front, people most often feel it in the groin or the front of the hip, sometimes cupping the area with a C-shape of the hand, and clinicians even call this the “C-sign.” It is typically a deep ache that worsens when you load the joint: standing on that leg, pivoting, twisting, getting out of a car, or rotating the hip.
Osteoarthritis and, in younger or more active people, hip impingement are the usual drivers, and the joint often feels stiff first thing in the morning or after sitting. Tellingly, this pain can refer down to the knee, which fools people into thinking the knee is the problem, yet it rarely shoots in the long, travelling line that nerve pain does (healthdirect).
Lateral hip pain that bites when you lie on it: greater trochanteric pain syndrome
There is a third pattern that gets wrongly labelled as “sciatica” or “bursitis” more than almost any other: pain on the outer side of the hip, right over the bony point you can feel there.
This is greater trochanteric pain syndrome, an irritation of the tendons and bursa on the side of the hip, and it has a giveaway signature: it is at its worst when you lie on that side in bed at night, and when you load one leg at a time on stairs or getting up from a low chair (review of diagnosis and management). It is most common in women between about 40 and 60.
Because it sits higher and to the side rather than radiating down a line, it is neither true sciatica nor a joint problem in the groin, and it responds to a quite specific loading program rather than to nerve-focused treatment, which is why getting the label right actually changes what helps.
When it is genuinely both, and why that is common
Real bodies rarely read the textbook. It is entirely possible, and quite common past middle age, to have more than one of these at once, because they share risk factors and feed into each other:
- A stiff, arthritic hip changes how you walk, which overloads the tendons on the side and brings on trochanteric pain as well.
- A cranky lower back alters how the hip muscles fire, so a nerve problem and a hip problem can genuinely coexist.
- Weak gluteal control sits underneath several of these at once, which is why two people with “the same” pain can need different programs.
This is the honest reason self-diagnosis has limits: the question is often not “which one is it?” but “which one is driving the pain right now, and what is feeding it?” That is a question an examination answers far better than a symptom checklist.
How a physiotherapist separates nerve from joint in one session
This is where a hands-on assessment earns its keep, because the two problems respond to different provocations. A physiotherapist will use nerve-tension tests, moving the leg and spine in ways that gently load the sciatic nerve, such as a straight-leg raise or a slump test, to see whether the familiar travelling pain reproduces.
Then they will use hip-specific tests, including the figure-4 (FABER) position and rotating the loaded hip, to see whether the groin or joint pain lights up instead. Pressing directly over the bony point on the side quickly flags trochanteric pain. Add in how your back moves, your walking pattern and your strength, and a clear picture usually emerges within a single visit of whether this is a nerve story, a joint story, or a bit of both.
That clarity is the whole point: it decides whether your plan should calm a nerve, unload a joint, or rebuild control on the side of the hip.
Red flags: when “hip or nerve” is not the real question
A small number of warning signs mean the priority is not sorting hip from sciatica but getting prompt medical review. See a doctor rather than waiting if any of these are present:
- Loss of bladder or bowel control, or numbness around the saddle area: this is a medical emergency, and the detail of why is covered in our sciatica guide above.
- Pain after a significant fall, or an inability to put weight through the leg, which can signal a fracture, especially in older adults.
- Fever, unexplained weight loss, night pain or a history of cancer alongside the pain, which warrant a medical opinion before starting exercise.
These are uncommon, and ordinary hip or sciatic pain does none of them. But they are worth knowing, because they are the situations where the usual “travels or sits still” reasoning no longer applies.
Pinning down the cause with Befit Physio in Carlingford and North Kellyville
If you have been guessing at your own buttock, hip or leg pain for weeks, an assessment replaces the guesswork with an answer and a plan. We untangle these overlapping patterns regularly, and naming the real driver early usually means a faster, less frustrating recovery.
Settling a nerve, unloading a hip and rebuilding the muscles that support both are all part of our back and neck pain physiotherapy, and for the day-to-day side of calming a lower-back flare, our practical tips for easing lower-back pain are a sensible place to start.
You can be seen at our Carlingford physiotherapy clinic or with our North Kellyville physiotherapists, in the clinic or at home.
| Not sure if it’s your hip or your sciatica? Book a one-on-one assessment online, or call Carlingford on 02 9872 2005 or North Kellyville on 02 9624 2047. We will find the real source and build the plan that fits it. |
Frequently asked questions
How do I know if it is sciatica or my hip?
Start with where the pain travels. If it shoots from the buttock down the back of the leg and past the knee, often with pins and needles or numbness, it is more likely sciatica. If it sits in the groin or the front of the hip and worsens when you load or rotate the leg, it is more likely the hip joint; if it is on the outer side and bites when you lie on it, it points to the tendons and bursa there. The rules overlap in the buttock, so a physiotherapist’s examination is what settles a genuinely unclear case.
Can a physiotherapist tell whether it is my hip or a nerve?
Yes, and usually within one appointment. A physiotherapist uses nerve-tension tests such as a straight-leg raise or slump test to provoke sciatic pain, and hip-specific tests such as the figure-4 position and loaded rotation to provoke joint pain, then reads your movement, walking pattern and strength. Because the two problems respond to different provocations, the pattern of what reproduces your pain usually makes the source clear.
What is the figure-4 (FABER) test for hip pain?
The figure-4 test, also called FABER, has you rest the ankle of the sore leg across the opposite knee so the hip bends, moves outward and rotates, forming a figure-4 shape. If this reproduces pain in the groin or hip, it suggests the joint or nearby structures rather than the sciatic nerve. It is one of several checks a physiotherapist uses together, not a standalone diagnosis, but it is a quick way to point towards a hip cause over a nerve one.
Can hip pain and sciatica happen at the same time?
They can, and it is fairly common past middle age. A stiff, arthritic hip changes how you walk and can overload the tendons on the side, while a lower-back problem can alter how the hip muscles work, so a nerve issue and a hip issue genuinely coexist. When that happens, the useful question is which one is driving most of the pain now and what is feeding it, which guides where treatment should focus first.
Which is usually more painful, hip bursitis or sciatica?
Neither is reliably worse than the other; it depends far more on the individual and the stage than on the label. Severe sciatica can be intensely sharp and limit almost everything, while trochanteric pain can be milder by day yet wreck your sleep because lying on that side is unbearable. Pain intensity is a poor way to tell them apart, which is why the pattern of where and when it hurts is the better guide.
About the author and clinical review
| Author: Anshu Sudan, Principal Physiotherapist and owner, Befit Physiotherapy & Sports Injury Centre (Masters of Physiotherapy, APA member). Clinically reviewed by: a physiotherapist at Befit Physio. Carlingford: Shop 2/1 Post Office St, Carlingford NSW 2118. North Kellyville: 15/21 Hezlett Rd, North Kellyville NSW 2155. |
| Medical disclaimer This article is general information, not personal medical advice, and reflects Australian guidance current as at October 2026. Buttock, hip and leg pain have several possible causes, so see a physiotherapist or doctor for an individual assessment and diagnosis before starting an exercise program. Seek urgent care for loss of bladder or bowel control, numbness in the saddle area, or an inability to weight-bear after a fall. |